Enhancing CVD Risk Assessment: Integrating Genetic Risk for Improved Prediction
In a population-based study, researchers found that both the relative genetic risk, assessed through a polygenic risk score and the absolute clinical risk, evaluated by SCORE2, independently contribute to an individual's overall CVD risk.
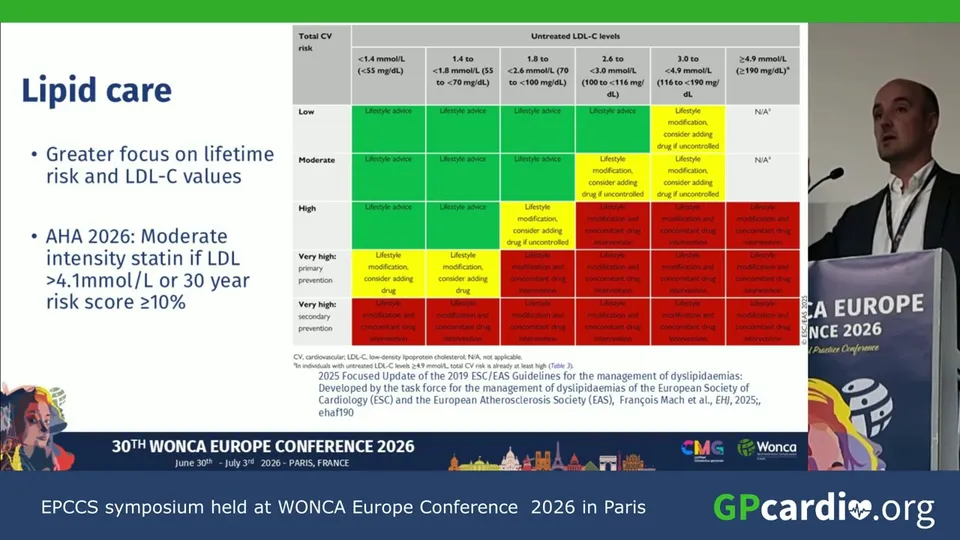
Clinical tools like SCORE2 help estimate an individual's absolute risk of CVD based on established risk factors. Conversely, PRSs measure an individual's genetic predisposition to CVD relative to the average population risk. However, current guidelines do not recommend using PRSs for risk assessment. This study aimed to understand how PRSs could complement existing clinical risk assessment tools.
Study Goals:
The authors assessed whether a factor measuring relative genetic risk (PRS-factor) can confer a constant relative risk across the spectrum of clinical risk and whether application of the PRS-factor can increase the precision of risk prediction in a clinically meaningful way for individuals at intermediate CVD risk as estimated by clinical risk assessment tools.
Methods:
Using data from 432,981 UK Biobank participants aged 40–69 years, researchers calculated PRSs for coronary artery disease (CAD) based on genetic and health-related data. They then categorized participants into deciles based on their PRS distribution to assess relative genetic risk (PRS-factor). The absolute clinical risk was estimated using SCORE2 and QRISK3. The stability of PRS-factor across different clinical risk categories was evaluated. Additionally, a new risk prediction model, "SCORE2 × PRS-factor = total risk," was developed and tested for risk reclassification in UK Biobank participants and validated in other population studies.
Main Results
- PRS-factor exhibited a consistent increase in relative risk of CVD across different PRS deciles, irrespective of traditional risk factors or clinical risk categories.
- Incorporating PRS-factor into risk prediction models significantly reclassified individuals, particularly those at intermediate clinical risk. This reclassification identified more individuals as high risk, resulting in a substantial increase in the number of individuals considered at high CVD risk.
- Individuals reclassified as high risk based on the new model had a significantly higher incidence of CVD events compared to those remaining at intermediate risk
Conclusion
The study highlights the independent contributions of relative genetic risk (PRS-factor) and absolute clinical risk (SCORE2) to overall CVD risk. Integrating PRS information into clinical risk assessment can improve risk prediction, especially for individuals at intermediate clinical risk but high genetic risk. This suggests a potential role for intensified preventive treatment in this population
Join us
Join the Global Primary Care Cardio Network. Membership is free.
Would you like to tell us more about yourself?
Interests
We will send you an email with a link to confirm your registration.